
About this series. Oral Hygiene is an eleven-part series on looking after teeth and gums at every age, from brushing and flossing to children’s teeth, gum disease and toothache.
This is Part 9: Pyorrhea (Gum Disease).
Healthy gums are an essential part of good oral health. They support and protect the teeth and the tissues surrounding them. However, inadequate oral hygiene can allow bacterial plaque to accumulate around the teeth and gums, leading to inflammation and infection.
Gum disease, also known as periodontal disease, refers to inflammatory conditions affecting the gums and the supporting tissues around the teeth. The two most common forms are gingivitis and periodontitis.
Gingivitis is generally the milder and reversible form, whereas periodontitis is a more advanced condition that can damage the periodontal ligament and alveolar bone and may eventually result in tooth loss.
The good news is that gum disease can often be prevented or controlled through proper oral hygiene, professional dental care and management of contributing risk factors.
At a Glance
Gum disease, also known as periodontal disease, refers to inflammatory conditions affecting the gums and the supporting tissues around the teeth. “Pyorrhea” is not a specific medical diagnosis, but the term is commonly used to describe symptoms of gum disease.
Gingivitis is generally reversible with proper oral hygiene and professional dental care. Periodontitis causes destruction of the tissues and bone supporting the teeth; the bone that has already been lost generally does not grow back on its own.
Bleeding gums should not simply be considered “normal.” Home care is important for maintaining healthy gums, but it should be viewed as supportive care, not a cure for periodontal disease.
Is Pyorrhea the Same as Gum Disease?
“Pyorrhea” (also spelled pyorrhoea or pyria) is not a specific medical diagnosis, but the term is commonly used to describe symptoms of gum disease. People may use “pyorrhea” when referring to bleeding gums, swollen gums, bad breath, pus around the gums, gum recession, or loose teeth.
Medically, gum disease is mainly classified as gingivitis and periodontitis:
- Gingivitis: Inflammation of the gums, usually caused by plaque buildup. It is generally reversible with proper oral hygiene and professional dental care.
- Periodontitis: A more advanced form of gum disease that damages the tissues supporting the teeth and can cause bone loss, gum recession, tooth mobility, and eventually tooth loss.
So, pyorrhea and gum disease are not exactly the same thing. “Pyorrhea” is a commonly used, non-specific term, while gingivitis and periodontitis are the medically appropriate terms used to diagnose and describe gum disease.
What Is Gum Disease?
Gum disease is an inflammatory condition caused primarily by the accumulation of dental plaque, a sticky bacterial biofilm that forms continuously on the teeth.
When plaque is not adequately removed, it can harden into calculus (tartar). Unlike plaque, calculus cannot be removed effectively with ordinary brushing and flossing and generally requires professional dental cleaning.
Persistent plaque and calculus accumulation can cause inflammation of the gingiva, resulting in gingivitis. If inflammation progresses and affects the deeper supporting structures of the teeth, the condition may develop into periodontitis.
Gingivitis vs Periodontitis
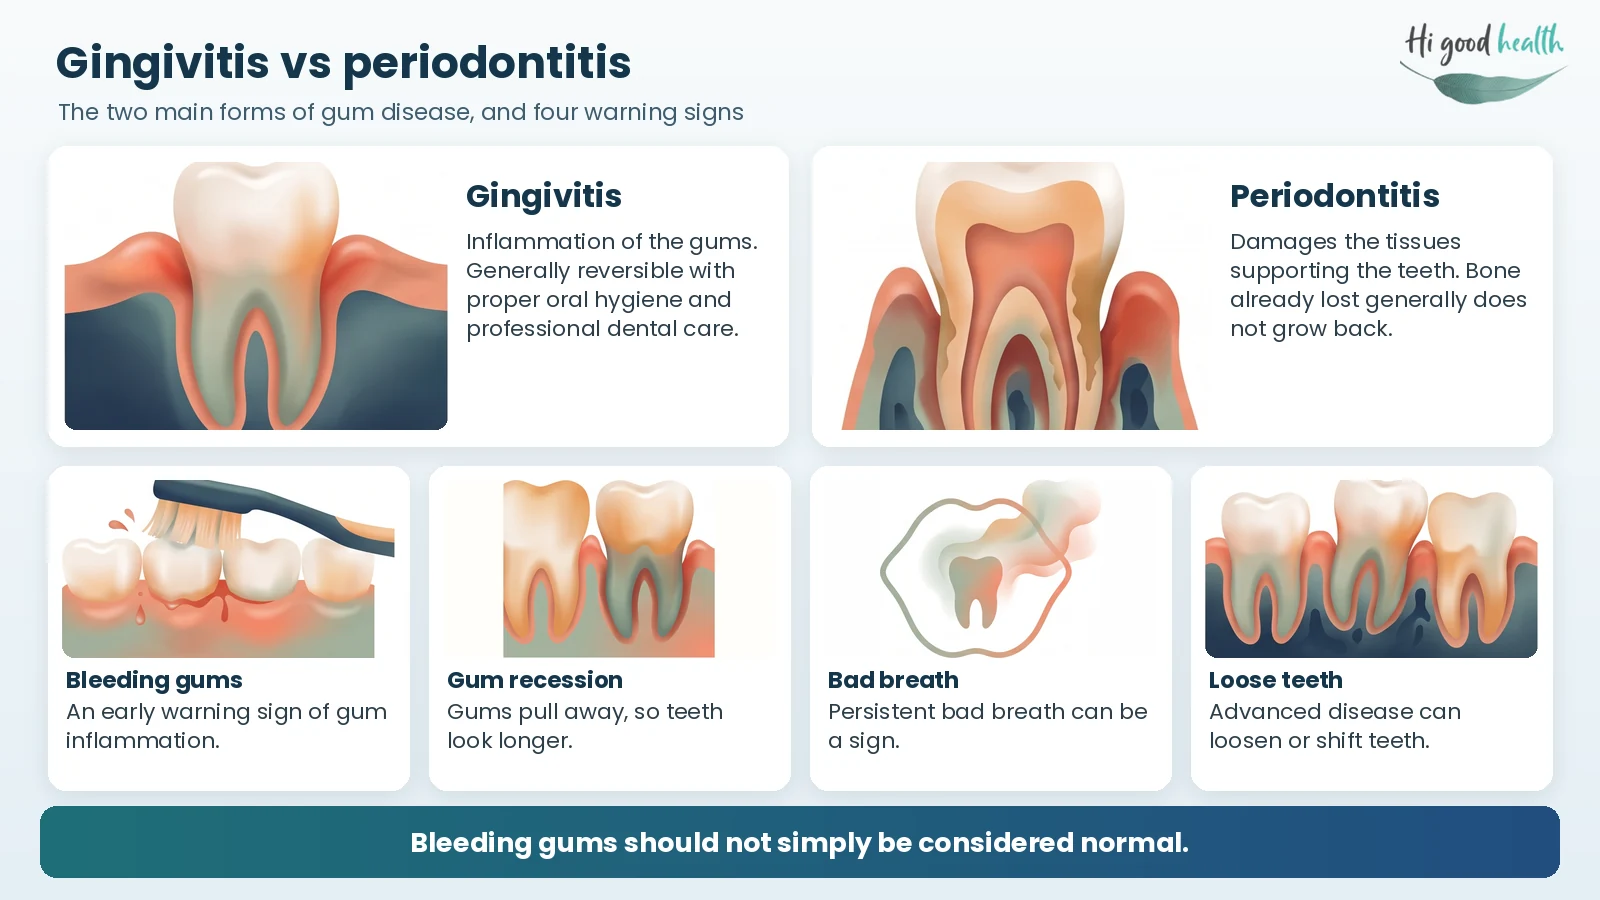
| Feature | Gingivitis | Periodontitis |
|---|---|---|
| Main affected tissue | Gingiva | Periodontium |
| Inflammation | Present | Present |
| Bone loss | Usually absent | May occur |
| Gum pockets | No pathological attachment loss | Periodontal pockets may develop |
| Reversible | Generally reversible | Usually manageable but existing attachment/bone loss is not completely reversible |
| Tooth mobility | Usually absent | May occur in advanced disease |
| Tooth loss | Not usually | Can occur in advanced disease |
Types of Gum Disease
Gum diseases can be broadly classified according to their clinical presentation and underlying cause.
1. Gingivitis
Gingivitis is inflammation of the gums without the loss of periodontal attachment.
It is commonly associated with plaque accumulation. The gums may become:
- Red or darker than usual
- Swollen
- Tender
- Prone to bleeding during brushing or flossing
Gingivitis is usually reversible with proper oral hygiene and professional dental treatment because there is no permanent loss of the supporting tissues.
Common causes of gingivitis:
- Inadequate brushing
- Inadequate interdental cleaning
- Plaque accumulation
- Calculus deposits
- Smoking or tobacco use
- Hormonal changes
- Certain medications
- Poorly fitting dental restorations
- Some systemic conditions
2. Periodontitis
Periodontitis is a chronic inflammatory disease involving the supporting structures of the teeth. It can lead to periodontal attachment loss and destruction of alveolar bone.
As the disease progresses, the gums may detach from the teeth, creating periodontal pockets that can harbor bacteria. Continued inflammation can result in bone destruction, tooth mobility and eventually tooth loss.
Periodontitis, however, causes destruction of the tissues and bone supporting the teeth; the bone that has already been lost generally does not grow back on its own. This is why recognizing and treating gum disease at the gingivitis stage is so important.
Modern periodontal classification assesses periodontitis using factors such as stage and grade, which help clinicians determine disease severity, complexity and risk of progression. The European Federation of Periodontology (EFP) provides evidence-based treatment pathways for different stages of periodontitis.
3. Necrotizing Periodontal Diseases
Necrotizing periodontal diseases are less common but more rapidly destructive conditions. They can cause:
- Severe gum pain
- Spontaneous bleeding
- Ulceration or necrosis of gingival tissues
- Foul odor
- Rapid tissue destruction
They are more likely to occur in individuals with certain systemic or immune-related risk factors and require prompt professional treatment.
4. Gum Problems Associated With Systemic Conditions
Some systemic diseases and conditions can increase susceptibility to gum disease or influence its severity.
For example, diabetes is associated with an increased risk of periodontal disease, particularly when blood glucose is poorly controlled. At the same time, periodontal inflammation may make blood glucose management more difficult.
What Causes Gum Disease?
The primary cause of plaque-induced gum disease is the accumulation of dental plaque.
Plaque contains bacteria that interact with the host immune system and can trigger inflammation in the gingival tissues. If plaque is not removed regularly, it may mineralize and form calculus.
Major causes and contributing factors include:
1. Poor Oral Hygiene
Inadequate brushing and interdental cleaning allow plaque to accumulate around the teeth and gumline.
2. Dental Calculus
Calculus provides a rough surface that can facilitate plaque retention. Professional cleaning is required to remove hardened calculus.
3. Smoking and Tobacco Use
Smoking is one of the most important modifiable risk factors for periodontal disease. Tobacco use can also impair healing and negatively affect periodontal treatment outcomes.
Gutkha, khaini, zarda and other tobacco products can cause vasoconstriction and reduce blood flow to the gums. As a result, gum bleeding may be reduced or masked even when periodontal disease is progressing.
This can give patients a false impression that their gums are healthy or improving, potentially delaying dental evaluation and allowing further damage to the supporting tissues and bone.
4. Diabetes
People with diabetes, particularly when it is poorly controlled, have an increased risk of periodontal problems.
5. Hormonal Changes
Hormonal changes during puberty, menstruation, pregnancy and other stages of life can increase gingival sensitivity and inflammatory responses to plaque.
6. Genetic Susceptibility
Genetic factors can influence an individual’s susceptibility to periodontal disease and its progression.
7. Certain Medications
Some medications may contribute to gingival enlargement or alter the oral environment, potentially making plaque control more difficult.
8. Stress and Other Health Conditions
Stress and certain systemic conditions may influence immune responses and oral health. NIDCR also identifies several medical conditions and medications among factors associated with periodontal disease.
Risk Factors for Gum Disease
A person may have a higher risk of developing gum disease if they have:
- Poor oral hygiene
- Smoking or tobacco use
- Diabetes
- Family history of periodontal disease
- Poorly controlled systemic diseases
- Certain medications
- Hormonal changes
- Poor nutrition
- High levels of stress
- Inadequate dental care
- Previous history of periodontal disease
It is important to remember that having a risk factor does not necessarily mean that a person will develop gum disease, but it may increase susceptibility.
Signs and Symptoms of Gum Disease
Gum disease can sometimes progress with relatively few symptoms, especially during the early stages. Therefore, regular dental examinations are important.
Common warning signs include:
1. Bleeding Gums
Bleeding while brushing, flossing or eating hard foods can be an early warning sign of gingival inflammation.
2. Red or Swollen Gums
Healthy gums are generally firm and do not appear persistently swollen or inflamed.
3. Gum Tenderness
Inflamed gums may feel sore or tender.
4. Persistent Bad Breath
Persistent halitosis may occur due to bacterial accumulation and periodontal inflammation.
5. Gum Recession
The gums may gradually pull away from the teeth, making teeth appear longer.
6. Increased Tooth Sensitivity
Exposed root surfaces resulting from gum recession can make teeth more sensitive to cold or hot foods and drinks.
7. Periodontal Pockets
In periodontitis, the space between the gum and tooth can become deeper due to loss of attachment.
8. Loose or Shifting Teeth
Advanced periodontal destruction can compromise the supporting tissues of the teeth, leading to mobility or changes in tooth position.
9. Pain or Difficulty While Chewing
Advanced periodontal disease may cause discomfort during chewing.
Important: Bleeding gums should not simply be considered “normal.” Frequent or unexplained gum bleeding should be evaluated by a dentist.
How Is Gum Disease Diagnosed?
A dentist or periodontist usually combines clinical examination with a detailed medical and dental history.
1. Clinical Examination
The dentist examines:
- Gum color and appearance
- Swelling and inflammation
- Plaque and calculus
- Gum recession
- Tooth mobility
- Signs of infection
2. Periodontal Probing
A periodontal probe is used to measure the depth of the spaces around the teeth.
Healthy periodontal pockets are generally around 1–3 mm without bleeding or attachment loss. Increased probing depths may indicate periodontal disease and require interpretation alongside other clinical findings.
3. Assessment of Clinical Attachment
The dentist may measure clinical attachment levels to determine whether periodontal attachment has been lost.
4. Dental X-rays
Radiographs can help identify the amount and pattern of bone loss around teeth.
5. Medical History
Conditions such as diabetes, smoking and certain medications may affect periodontal health and treatment planning.
Treatment of Gum Disease
Treatment depends on the type and severity of gum disease, the patient’s risk factors and their overall oral and systemic health.
Treatment of Gingivitis
Early gingivitis can often be controlled or reversed with improved plaque control.
Treatment may include:
- Professional dental cleaning
- Twice-daily toothbrushing with fluoride toothpaste
- Daily interdental cleaning
- Improvement of brushing technique
- Removal of calculus
- Management of contributing factors
- Tobacco cessation
NIDCR recommends brushing twice daily and regular interdental cleaning to help control plaque.
Treatment of Periodontitis
Periodontitis requires professional periodontal management.
1. Patient Education and Oral Hygiene. The first step is helping the patient understand the disease and improve daily plaque control.
The dentist may recommend:
- Appropriate brushing technique
- Dental floss
- Interdental brushes
- Water flossers where appropriate
- Fluoride toothpaste
- Regular dental visits
The choice of interdental cleaning method should be individualized according to interdental spaces, dexterity and periodontal condition.
2. Scaling and Root Surface Instrumentation. Professional periodontal cleaning removes plaque and calculus from above and below the gumline.
Scaling and root planing/root surface instrumentation can help reduce the bacterial burden and inflammation in periodontal pockets.
3. Adjunctive Antimicrobial Therapy. In selected cases, dentists may use antimicrobial agents as an adjunct to mechanical periodontal treatment.
These may include specific mouth rinses or locally/systemically delivered medications depending on the patient’s condition.
Antibiotics should not be used routinely for every case of gum disease. Their use should be based on professional assessment and appropriate clinical indications.
4. Periodontal Surgery. If deep periodontal pockets or persistent disease remain after non-surgical treatment, periodontal surgery may be considered.
Depending on the clinical situation, procedures may include:
- Flap surgery
- Regenerative periodontal procedures
- Bone grafting
- Guided tissue regeneration
- Soft-tissue procedures
Advanced periodontal cases may require multidisciplinary management. The EFP provides specific evidence-based recommendations for stages I–III and stage IV periodontitis.
5. Maintenance Therapy. Periodontal treatment does not end after scaling or surgery.
Patients with periodontitis require long-term periodontal maintenance, including regular professional monitoring and continued plaque control at home.
Does Scaling Loosen Teeth or Create Gaps?
No. Dental scaling does not loosen healthy teeth, wear away enamel, or create gaps between teeth. Scaling removes plaque and hardened tartar (calculus) that has accumulated around the teeth and gums.
Sometimes, patients notice small gaps appearing after scaling. These gaps were often already present but were hidden by tartar deposits or swollen, inflamed gums.
Once the deposits are removed and the gum inflammation settles, the natural spaces between the teeth may become more visible. This is not damage caused by scaling; rather, it reveals the actual condition of the teeth and gums.
Home Remedies and Ayurvedic Treatments for Gum Disease: What Helps and What Doesn’t?
Some home measures can support oral hygiene and provide temporary relief from mild gum irritation, but they cannot replace professional treatment, especially in periodontitis.

What Patients Can Safely Do at Home
- Brush twice daily with a soft-bristled toothbrush and fluoride toothpaste.
- Clean between the teeth daily using floss or appropriately sized interdental brushes.
- Warm salt-water rinses may temporarily soothe irritated or inflamed gums.
- Maintain a balanced diet and limit frequent sugary snacks and drinks.
- Stay well hydrated.
- Continue regular dental check-ups and professional cleaning as recommended.
If you are waiting for a dental appointment, these measures can help maintain oral cleanliness and reduce discomfort.
What About Ayurvedic Remedies and Oil Pulling?
- Oil pulling: May contribute to oral cleanliness, but evidence is insufficient to consider it a treatment for established gum disease. It should not replace brushing or interdental cleaning.
- Clove oil: Eugenol may provide temporary relief from dental discomfort, but concentrated clove oil can irritate or burn oral tissues. It should not be applied directly in an undiluted form.
- Herbal tooth powders: Some may help with cleaning, but evidence varies considerably between products. Abrasive powders may cause enamel wear or gum irritation when used aggressively.
- Charcoal-based products: There is limited evidence that they provide additional periodontal benefits, and some may be abrasive.
- Alum: Although traditionally used for its astringent properties, frequent or concentrated use can irritate oral tissues and should not be relied upon to treat gum disease.
What Home Remedies Cannot Do
- Remove hardened tartar/calculus, particularly below the gumline.
- Eliminate deep periodontal pockets.
- Treat established periodontitis on their own.
- Reverse or regenerate bone that has already been lost.
- Replace professional scaling and periodontal treatment.
- Prevent disease progression if significant periodontal disease is left untreated.
When Can Home Remedies Become Harmful?
Home care becomes a concern when it delays necessary professional treatment. Seek a dental evaluation if there is:
- Persistent or spontaneous gum bleeding
- Swollen or painful gums
- Pus or discharge from the gums
- Persistent bad breath
- Gum recession
- Loose or shifting teeth
- Pain while chewing
- Increasing spaces between teeth
- A history of diagnosed periodontitis
The key message: Home care is important for maintaining healthy gums, but it should be viewed as supportive care, not a cure for periodontal disease. Natural or Ayurvedic does not automatically mean risk-free, and persistent symptoms should always be evaluated by a dental professional.
Can Gum Disease Be Prevented?
In many cases, the risk of gum disease can be significantly reduced through consistent oral hygiene and regular dental care.
Follow these steps:
- Brush twice daily. Use a fluoride toothpaste and an appropriate toothbrush.
- Clean between your teeth daily. Use dental floss, interdental brushes or another method recommended by your dentist.
- Have regular dental check-ups. Professional examinations can detect gingivitis and periodontal disease at an early stage.
- Get professional cleaning when required. Calculus cannot be effectively removed with ordinary brushing.
- Avoid tobacco products. Stopping tobacco use can improve periodontal health and treatment outcomes.
- Control systemic conditions. Good management of conditions such as diabetes is important for overall and periodontal health.
- Do not ignore bleeding gums. Persistent bleeding should be evaluated rather than treated as a normal occurrence.
What Happens If Gum Disease Is Left Untreated?
Untreated gum disease can progress from gingival inflammation to periodontal tissue destruction.
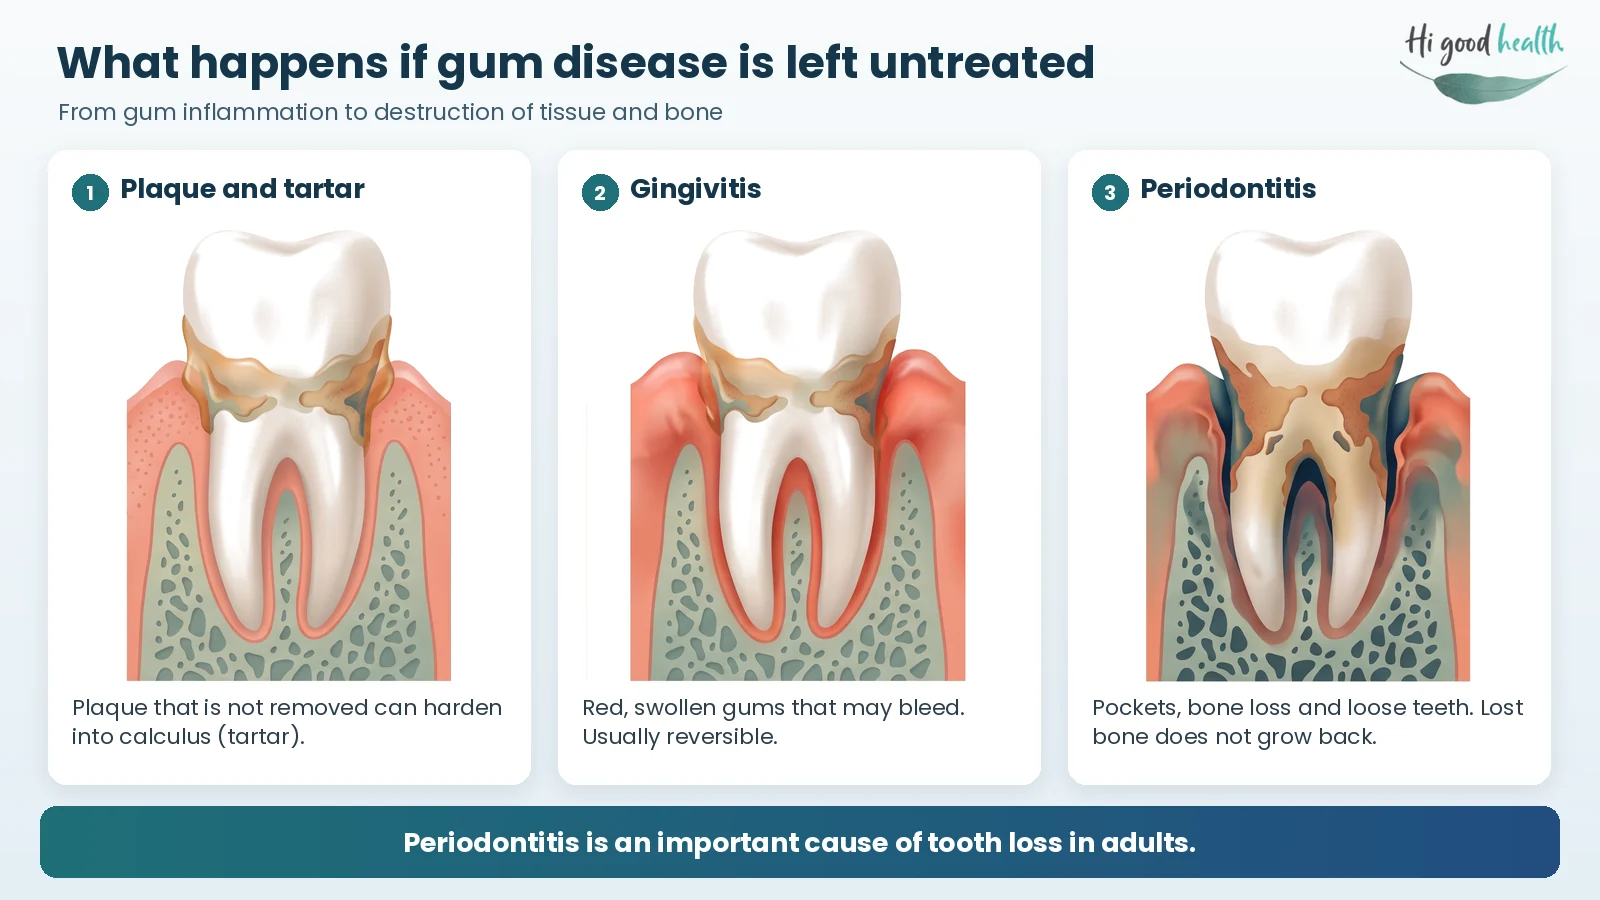
Advanced periodontitis may cause:
- Periodontal pocket formation
- Gum recession
- Bone loss
- Tooth mobility
- Tooth migration
- Difficulty chewing
- Tooth loss
Periodontitis is an important cause of tooth loss in adults.
Gum Disease and Overall Health
The relationship between periodontal disease and general health is an active area of research.
Periodontal disease has been associated with several systemic conditions, including diabetes and cardiovascular conditions. However, an association does not automatically mean that periodontal disease directly causes these diseases.
One well-established clinical relationship is with diabetes: people with poorly controlled diabetes have an increased risk of periodontal disease, while periodontal inflammation can make blood glucose control more difficult.
Therefore, maintaining good oral health should be considered an important part of overall healthcare.
Frequently Asked Questions About Pyorrhea and Gum Disease
Is pyorrhea (gum disease) contagious?
Gum disease itself is not generally considered a contagious disease that spreads like a common infection. However, periodontal disease involves complex interactions between oral microorganisms and the individual’s immune response. Good oral hygiene remains important for maintaining a healthy oral microbiome.
Is bleeding while brushing normal?
No. Occasional bleeding may occur because of aggressive brushing or improper flossing, but persistent or recurrent bleeding is commonly a sign of gingival inflammation and should be evaluated by a dentist.
Can periodontitis be cured completely?
Periodontitis can often be effectively controlled and managed, but the bone and periodontal attachment already lost because of the disease do not spontaneously return to their original condition. Treatment aims to control inflammation, stop or slow progression and preserve the remaining periodontal support.
Is scaling harmful to the teeth?
Professional scaling is a routine procedure used to remove plaque and calculus. When appropriately performed, it is an important part of periodontal care. Temporary sensitivity may occur in some patients, particularly when deposits have been covering exposed root surfaces.
Can brushing alone prevent gum disease?
Brushing is essential, but it does not adequately clean all interdental areas. Daily interdental cleaning is important for removing plaque from areas that a toothbrush cannot reach effectively.
Is mouthwash enough to treat gum disease?
No. Mouthwash should not be considered a substitute for mechanical plaque removal. Depending on the condition, a dentist may recommend a therapeutic mouthwash as an adjunct to brushing and interdental cleaning.
Can gum disease come back after treatment?
Yes. Periodontitis is a chronic condition that requires long-term maintenance. Without continued plaque control and professional periodontal care, inflammation and disease progression may recur.
When should I see a dentist?
Consult a dentist if you experience recurrent bleeding gums, swollen or painful gums, persistent bad breath, gum recession, loose teeth, pus around the gums, pain while chewing or changes in tooth position. Early diagnosis generally allows simpler management and helps prevent further periodontal destruction.
The Oral Hygiene Series
Eleven articles on looking after your teeth and gums, at every age.
- Complete Oral Hygiene Guide for Every Age — the whole routine, age by age
- Brushing Technique: Bass, Modified Bass and Fones — which method suits which mouth, and how long two minutes really is
- Electric vs Manual Toothbrush — what the evidence shows, rather than what the manufacturers claim
- How to Floss Correctly — step by step, including the C-shape wrap and how far below the gumline to go
- Water Flosser for Tonsil Stones — what pressure is safe, and when not to try it at all
- Interdental Brushes and Bleeding Gums — choosing the right size, and why bleeding usually stops within two weeks
- Early Childhood Caries — causes, symptoms, prevention and treatment in children under six
- Milk Teeth Falling Out — the age, order and timeline, and what parents should know
- Pyorrhea (Gum Disease) — causes, symptoms, treatment and prevention (you are here)
- Gum Swelling, Bleeding and Dry Mouth — how underlying diseases affect your gums and oral health
- Medicine for Toothache — what to take, what causes the pain, and how it is treated
Key Takeaways
Healthy gums should not routinely bleed, remain swollen or cause persistent discomfort.
Gum disease commonly begins with plaque-induced gingival inflammation. When managed early, gingivitis is generally reversible. However, untreated periodontal inflammation can progress to periodontitis, resulting in attachment and bone loss, tooth mobility and eventually tooth loss.
The best approach is prevention, early diagnosis, professional treatment and lifelong periodontal maintenance. Brushing twice daily with fluoride toothpaste, cleaning between the teeth, avoiding tobacco, controlling systemic risk factors and attending regular dental examinations can all contribute to healthier gums.
If you notice persistent bleeding, swelling, recession, bad breath or loose teeth, do not wait for symptoms to worsen: consult a dentist or periodontist.
Glossary
- Dental plaque: a sticky bacterial biofilm that forms continuously on the teeth.
- Calculus (tartar): When plaque is not adequately removed, it can harden into calculus (tartar).
- Gingivitis: inflammation of the gums without the loss of periodontal attachment.
- Periodontitis: a chronic inflammatory disease involving the supporting structures of the teeth.
- Periodontal pockets: In periodontitis, the space between the gum and tooth can become deeper due to loss of attachment.
- Scaling: Scaling removes plaque and hardened tartar (calculus) that has accumulated around the teeth and gums.
References
All links checked and working on 28 September 2026.
- National Institute of Dental and Craniofacial Research (NIDCR). Periodontal (Gum) Disease. NIDCR: Periodontal (Gum) Disease
- Centers for Disease Control and Prevention (CDC). About Oral Health. CDC: About Oral Health
- European Federation of Periodontology (EFP). Guideline on Treatment of Stage I–III Periodontitis. EFP stage I–III guideline
- European Federation of Periodontology. Guideline on Treatment of Stage IV Periodontitis. EFP stage IV guideline
- NIDCR. Oral Hygiene. National Institutes of Health. NIDCR: Oral Hygiene
- NIDCR. Diabetes and Oral Health. NIDCR: Diabetes and Oral Health
- Herrera D, Sanz M, Kebschull M, et al. Treatment of stage I–III periodontitis: The EFP S3 level clinical practice guideline. Journal of Clinical Periodontology. 2020.
Disclaimer
This content is for educational purposes only and is not a substitute for professional medical or dental advice. Always consult a dentist or other qualified healthcare provider about gum problems and their treatment.
