
The mouth is not separate from the rest of the body. Oral tissues can be affected by systemic diseases, medications, nutritional deficiencies and hormonal changes. In some cases, oral changes may even be among the first signs that an underlying health problem requires attention.
Periodontal disease, commonly known as gum disease, is a chronic inflammatory condition affecting the tissues that support the teeth.
Although dental plaque is the primary initiating factor for plaque-induced gingivitis and periodontitis, the body’s systemic health can influence how the periodontal tissues respond to bacterial plaque and how quickly periodontal disease progresses.
Conditions such as diabetes, immune disorders, blood diseases, hormonal changes and certain nutritional deficiencies may increase susceptibility to oral and periodontal problems.
At the same time, periodontal disease is associated with several systemic conditions, particularly diabetes. This makes oral health an important component of overall healthcare.
At a Glance
Your mouth can reflect what is happening throughout your body. Although dental plaque is the primary initiating factor in most gingivitis and periodontitis, systemic diseases can influence the body’s immune response, inflammation, tissue healing, saliva production and susceptibility to infection.
The relationship between diabetes and periodontal disease works in both directions. Some medications used to treat systemic diseases can also cause oral side effects.
If persistent or unusual oral changes occur, they should not simply be attributed to poor oral hygiene. A dental examination may be the first step toward identifying the cause and ensuring appropriate medical or dental care.
Gum Swelling, Bleeding or Dry Mouth: When Should It Raise Concern About an Underlying Disease?
Certain oral findings should not be ignored, especially when they are persistent, unexplained or unusually severe.
Consult a dentist or physician if you experience:
- Persistent gum bleeding
- Sudden severe gum inflammation
- Unexplained gum enlargement
- Recurrent oral ulcers
- Persistent dry mouth
- Repeated oral infections
- Delayed wound healing
- Unexplained tooth mobility
- Persistent oral pain
- Unusual white, red or ulcerated lesions
- Significant changes in taste
- Recurrent infections despite good oral hygiene
These symptoms do not necessarily mean that an underlying systemic disease is present, but they may warrant further evaluation.
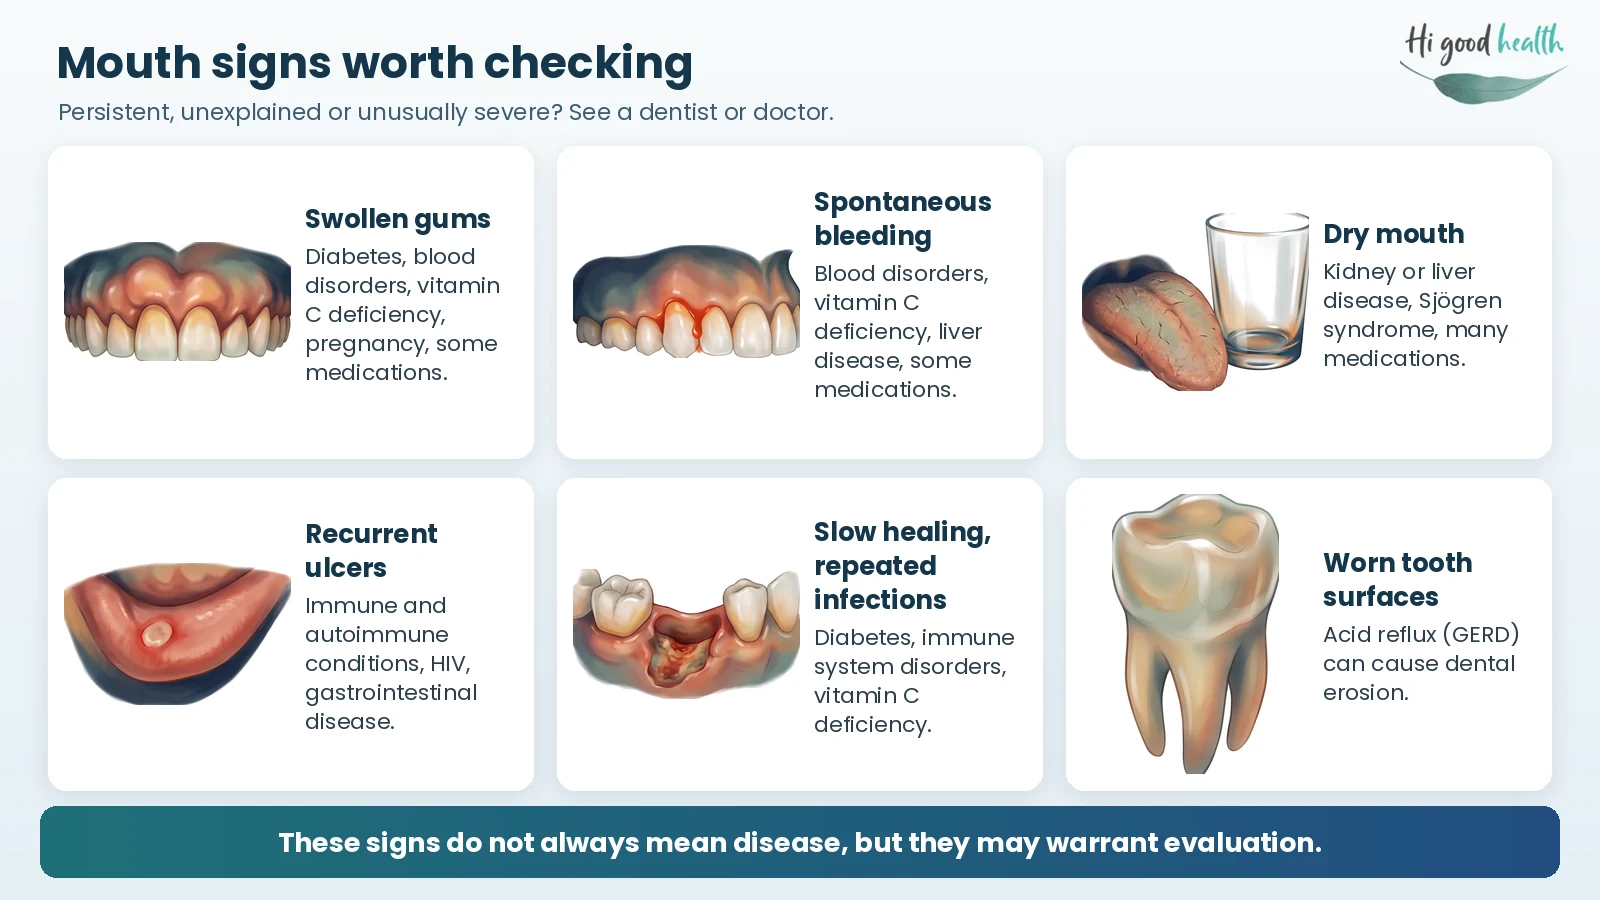
| What you may notice | Conditions in this article associated with it |
|---|---|
| Swollen or enlarged gums | Diabetes, leukaemia, vitamin C deficiency, pregnancy, some medications |
| Spontaneous or increased gum bleeding | Leukaemia, vitamin C deficiency, liver disease, some medications |
| Dry mouth | HIV infection, kidney disease, liver disease, Sjögren syndrome, many medications |
| Recurrent oral ulcers | Leukaemia, immune system disorders, HIV infection, autoimmune diseases, coeliac disease |
| Repeated infections or delayed healing | Diabetes, immune system disorders, vitamin C deficiency |
| Tooth sensitivity or worn tooth surfaces | Gastroesophageal reflux disease (GERD) |
How Can an Underlying Disease Affect the Gums?
The development and progression of periodontal disease depend on an interaction between:
Dental plaque + immune response + genetic susceptibility + systemic health + environmental factors
When bacteria accumulate around the teeth, the immune system responds to them. In susceptible individuals, an exaggerated or dysregulated inflammatory response can contribute to destruction of periodontal tissues.
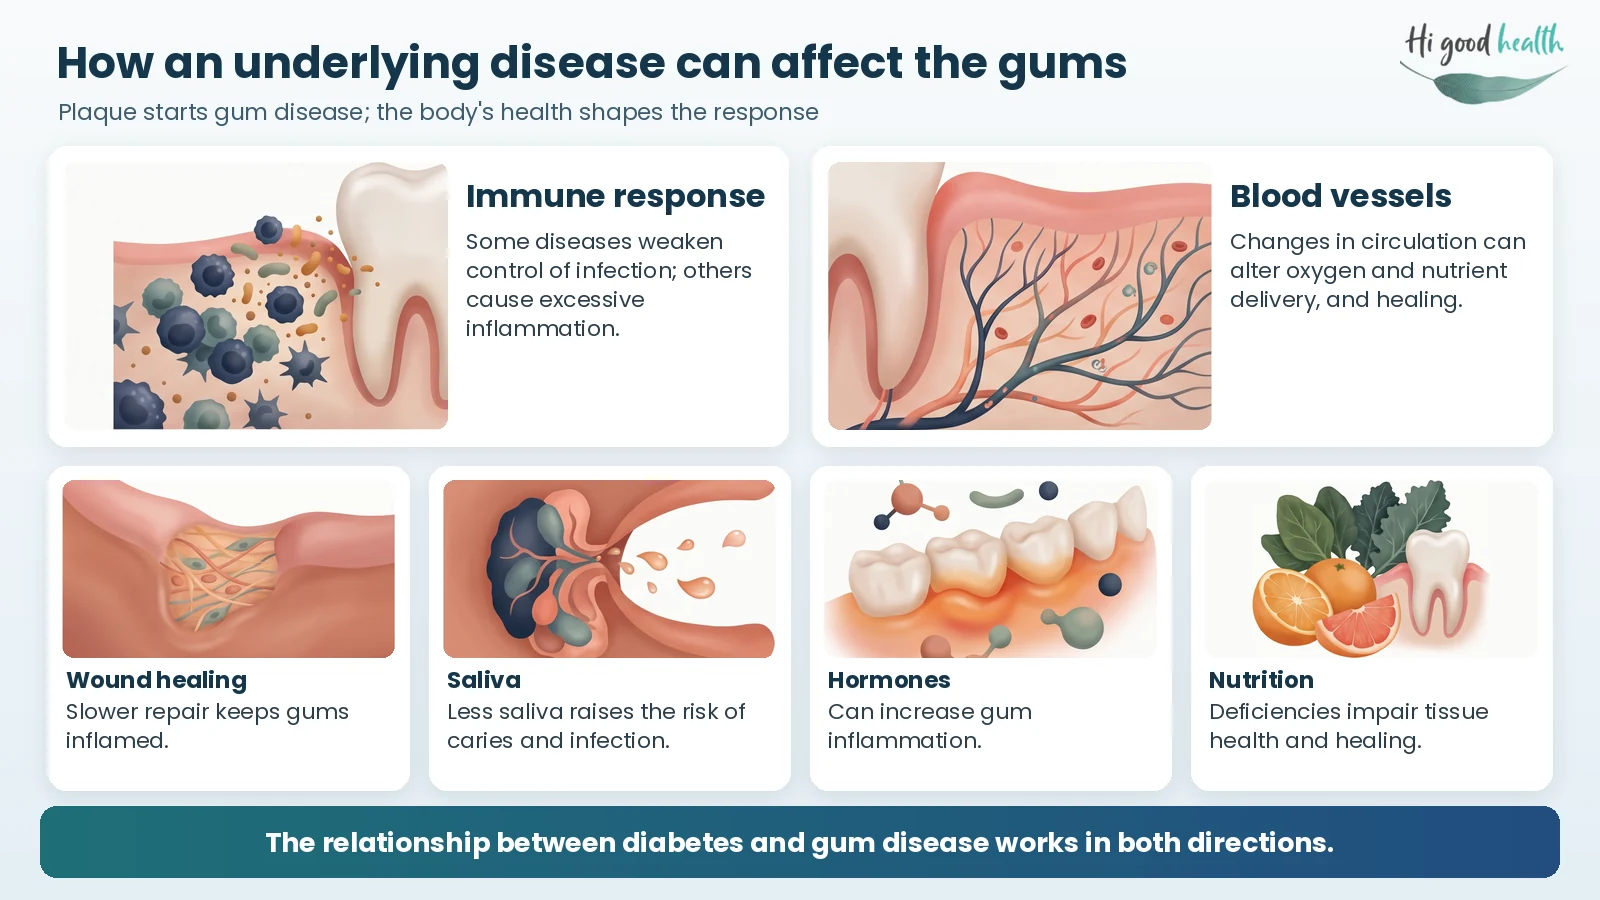
An underlying disease can influence this process in several ways:
- Altering the immune response: Some diseases impair the body’s ability to control bacterial infection, while others can cause excessive inflammatory responses.
- Affecting blood vessels and circulation: Conditions that affect blood vessels may alter the delivery of oxygen and nutrients to periodontal tissues and influence healing.
- Affecting wound healing: Certain systemic diseases can slow tissue repair, making the gums more vulnerable to persistent inflammation.
- Altering saliva: Some diseases and medications can reduce salivary flow. Reduced saliva can increase the risk of dental caries, oral infections, discomfort and difficulty maintaining oral hygiene.
- Causing hormonal changes: Hormonal fluctuations can alter the gingival response to plaque and may increase gum inflammation.
- Affecting nutrition: Nutritional deficiencies can impair tissue health and healing and may produce oral manifestations.
Systemic Diseases and Their Effects on Periodontal and Oral Health
1. Diabetes Mellitus
Diabetes is one of the most important systemic conditions associated with periodontal disease.
People with diabetes, particularly when blood glucose is poorly controlled, have an increased risk of developing periodontal disease.
How does diabetes affect the gums? Persistently elevated blood glucose can contribute to:
- Impaired immune response
- Increased inflammatory activity
- Altered blood vessel function
- Delayed wound healing
- Increased susceptibility to infections
These changes can make it more difficult for the body to control periodontal inflammation.
People with diabetes may experience:
- Red and swollen gums
- Bleeding gums
- Periodontal pockets
- Gum recession
- Increased periodontal destruction
- Delayed healing following dental procedures
- Increased risk of oral infections
The two-way relationship. The relationship between diabetes and periodontal disease works in both directions:
- Diabetes → increased risk of periodontal disease
- Periodontal inflammation → may adversely affect glycaemic control
Therefore, people with diabetes should include regular dental and periodontal examinations as part of their overall healthcare.
2. Cardiovascular Disease
Periodontal disease and cardiovascular diseases have been associated in numerous studies.
Chronic periodontal inflammation can contribute to systemic inflammatory burden, and periodontal bacteria or their components may enter the bloodstream.
However, it is important to distinguish association from causation.
Current evidence does not establish that treating periodontal disease prevents cardiovascular disease. Nevertheless, maintaining good oral health is an important part of general health, particularly in people who already have cardiovascular risk factors.
Oral considerations. Patients with cardiovascular disease may also take medications that affect oral health. Some medications can cause:
- Dry mouth
- Gingival enlargement
- Changes in taste
- Increased bleeding tendency
Dental professionals should therefore review the patient’s medical history and medications before treatment.
3. Blood Disorders
Several blood disorders can produce noticeable changes in the oral cavity.
Leukaemia. Leukaemia can affect blood cells and the immune system and may present with oral manifestations such as:
- Spontaneous gingival bleeding
- Enlarged or swollen gums
- Pale oral tissues
- Oral ulceration
- Increased susceptibility to infection
In some individuals, unexplained gingival enlargement or persistent oral changes may be an early indication of an underlying blood disorder.
Important: These findings are not specific to leukaemia and can occur with many other conditions. Persistent unexplained oral changes require medical evaluation.
4. Anaemia and Nutritional Deficiencies
Nutritional deficiencies can affect oral tissues.
Iron deficiency. Iron deficiency and anaemia may be associated with:
- Pale oral mucosa
- Soreness or burning of the tongue
- Atrophic changes of the tongue
- Cracks at the corners of the mouth
Vitamin C deficiency. Severe vitamin C deficiency can impair collagen formation and wound healing and may result in:
- Swollen gums
- Bleeding gums
- Poor wound healing
- Increased susceptibility to periodontal problems
A balanced diet containing adequate vitamins and minerals is therefore important for maintaining healthy oral tissues.
5. Immune System Disorders
The immune system plays a major role in periodontal health.
People with conditions that impair immune function may have increased susceptibility to:
- Oral infections
- Periodontal disease
- Fungal infections
- Ulcers
- Delayed healing
For example, individuals with significant immune suppression may develop infections that would be less common or less severe in people with normal immune function.
The severity of oral manifestations depends on the underlying condition, degree of immune suppression and other risk factors.
6. HIV Infection
HIV infection can affect the immune system and has been associated with several oral manifestations.
These may include:
- Oral candidiasis
- Oral ulcers
- Gingival inflammation
- Necrotising periodontal diseases
- Dry mouth
- Increased susceptibility to infections
With effective antiretroviral therapy and appropriate medical care, the prevalence and severity of many HIV-associated oral conditions have changed substantially.
7. Hormonal Changes
Hormonal fluctuations can alter the response of gingival tissues to dental plaque.
Puberty. During puberty, increased levels of sex hormones can exaggerate the gingival inflammatory response to plaque.
Pregnancy. Pregnancy can increase gingival sensitivity to plaque and may result in:
- Swollen gums
- Redness
- Bleeding during brushing
- Increased gingival inflammation
This is commonly referred to as pregnancy gingivitis.
Pregnancy itself does not cause plaque, but hormonal changes can modify the gingival response to existing plaque.
Maintaining good oral hygiene and receiving appropriate professional dental care during pregnancy are important.
8. Osteoporosis
Osteoporosis is characterised by reduced bone mass and deterioration of bone tissue.
Because the alveolar bone supports the teeth, researchers have investigated the relationship between osteoporosis and periodontal disease.
Although associations have been reported, osteoporosis should not be considered a direct cause of periodontitis. Periodontitis is primarily an inflammatory disease initiated by a dysbiotic dental biofilm in susceptible individuals.
Patients with osteoporosis may also receive medications that are relevant to dental treatment planning, particularly antiresorptive medications.
Therefore, patients should inform their dentist about all medications used for osteoporosis.
9. Kidney Disease
Chronic kidney disease can be associated with several oral changes.
Patients may experience:
- Dry mouth
- Altered taste
- Bad breath
- Oral mucosal changes
- Increased dental plaque and calculus
- Increased periodontal problems
Patients undergoing dialysis or those with advanced kidney disease may require individualised dental treatment planning in coordination with their medical team.
10. Liver Disease
Liver diseases can influence oral health in several ways.
Possible oral manifestations include:
- Increased tendency to bleed in some patients
- Dry mouth
- Altered taste
- Oral mucosal changes
- Increased risk of infection in certain circumstances
Because the liver plays an important role in producing clotting factors and metabolising many medications, significant liver disease should always be disclosed to the dentist before treatment.
11. Gastroesophageal Reflux Disease (GERD)
GERD occurs when stomach contents repeatedly flow back into the oesophagus.
Repeated exposure of teeth to gastric acid can contribute to dental erosion, particularly when reflux reaches the oral cavity.
Patients may notice:
- Tooth sensitivity
- Smooth or worn tooth surfaces
- Changes in tooth shape
- Increased sensitivity to hot and cold foods
Dental erosion is different from dental caries because erosion results primarily from chemical dissolution by acids rather than bacterial acid production.
Management involves controlling the underlying reflux along with appropriate dental preventive measures.
12. Autoimmune Diseases
Some autoimmune diseases can produce significant oral manifestations.
For example, Sjögren syndrome can reduce salivary gland function and cause persistent dry mouth.
Reduced saliva may increase the risk of:
- Dental caries
- Difficulty swallowing dry foods
- Oral discomfort
- Oral infections
- Difficulty speaking
- Altered taste
Other autoimmune diseases can produce oral ulcers, mucosal lesions or gingival changes.
Patients with persistent unexplained oral lesions should be evaluated by a dental or medical professional.
13. Gastrointestinal Diseases
Certain gastrointestinal disorders can have oral manifestations.
For example, coeliac disease may be associated with:
- Recurrent aphthous ulcers
- Enamel defects
- Delayed dental development in children
- Increased risk of certain oral problems
These findings are not diagnostic on their own, but persistent or unusual oral manifestations may warrant further medical investigation.
14. Neurological Conditions and Oral Health
Neurological conditions can indirectly affect oral health.
Difficulty with hand coordination, muscle control, swallowing, chewing and maintaining oral hygiene may make effective brushing and interdental cleaning more difficult.
Patients who have difficulty performing oral hygiene independently may benefit from assistance from caregivers and individualised preventive dental care.
15. Medications and Oral Health
Sometimes the underlying disease is not the only factor affecting oral health. Medications used to treat systemic diseases can also cause oral side effects.
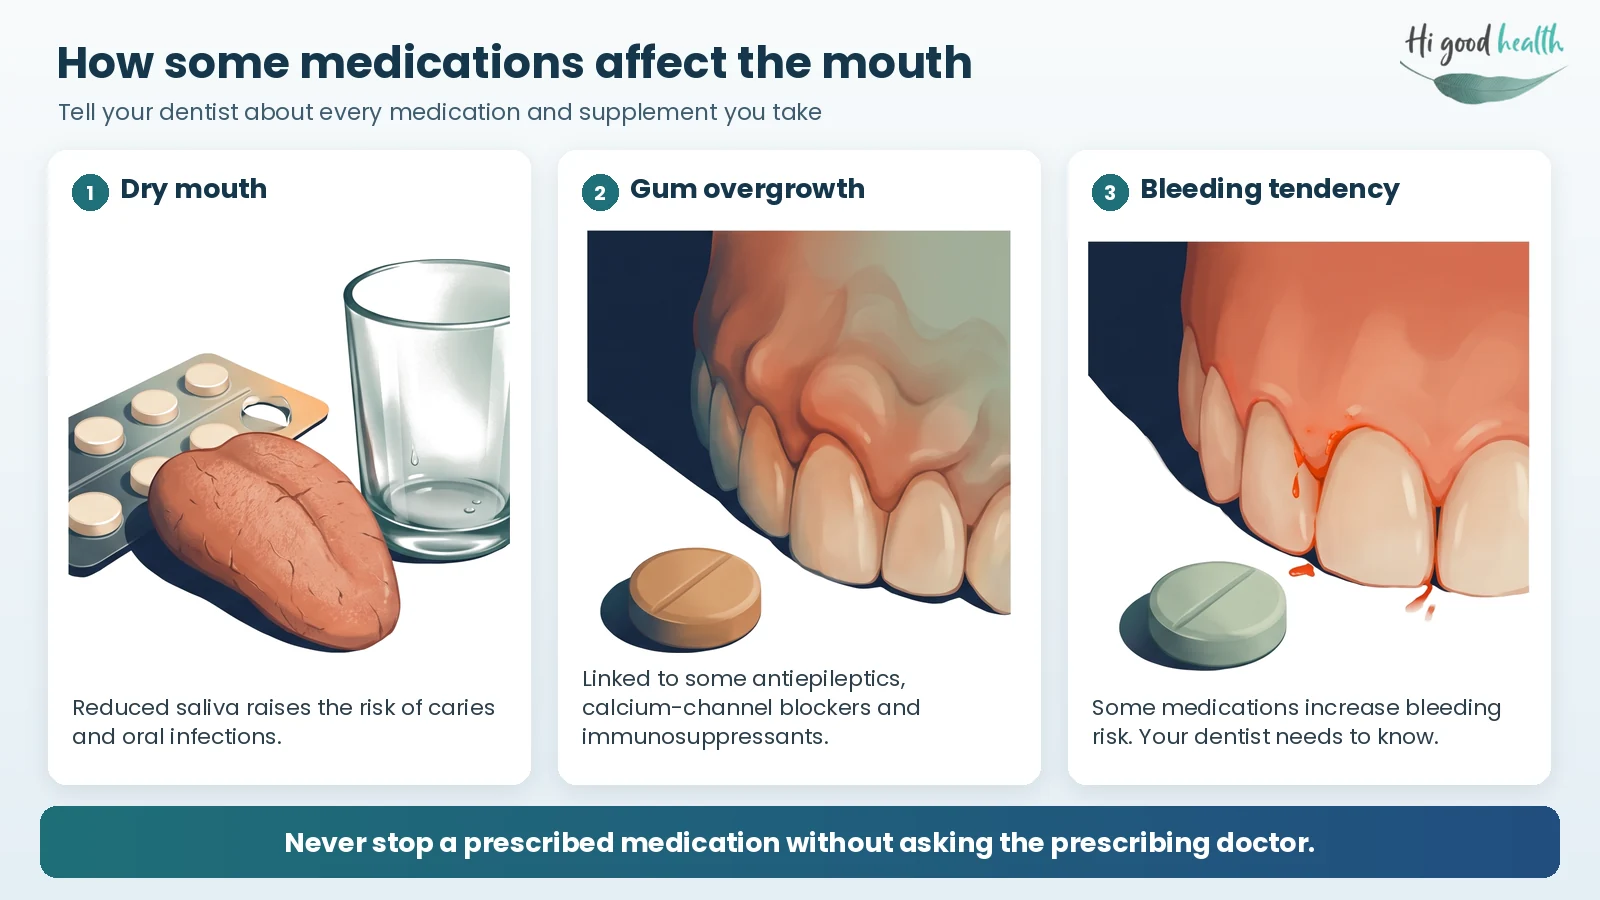
Some medications may cause:
- Dry mouth. Reduced saliva can increase the risk of caries, oral infections, difficulty swallowing and oral soreness.
- Gingival enlargement. Certain medications can cause gingival overgrowth. Examples include some antiepileptic medications, calcium-channel blockers and immunosuppressive medications.
- Increased bleeding tendency. Some medications can increase bleeding risk or alter platelet function. This does not necessarily mean that dental treatment cannot be performed, but the dentist needs to know about the medication.
Never stop a prescribed medication simply because of an oral side effect without consulting the prescribing doctor.
Can Periodontal Disease Affect the Rest of the Body?
The relationship between periodontal disease and systemic health is bidirectional and complex.
Periodontitis involves chronic inflammation of the tissues surrounding the teeth. Inflammation and bacterial products associated with periodontal disease can enter the circulation and contribute to systemic inflammatory responses.
Periodontal disease has been associated with conditions including:
- Diabetes
- Cardiovascular diseases
- Adverse pregnancy outcomes
- Respiratory conditions
- Rheumatoid arthritis
However, association does not necessarily prove that periodontal disease directly causes these conditions.
Diabetes is a particularly important example. The relationship between diabetes and periodontitis is supported by substantial evidence.
People with diabetes have an increased risk of periodontitis, while periodontal inflammation may adversely affect glycaemic control.
This is why oral healthcare should be integrated into the management of chronic systemic diseases.
How Can Dentists Help Identify Underlying Health Problems?
Dentists do more than examine teeth and gums.
During a dental examination, they may identify unusual oral findings that require further investigation.
A dentist may:
- Take a detailed medical history.
- Review current medications.
- Examine the gums and oral mucosa.
- Assess periodontal pocket depths.
- Evaluate tooth mobility and bone support.
- Take radiographs when indicated.
- Identify suspicious or unexplained oral lesions.
- Recommend medical evaluation or laboratory investigations when appropriate.
- Coordinate care with the patient’s physician.
This is one reason why regular dental check-ups are important even when there is no obvious toothache.
How to Protect Your Oral Health When You Have a Systemic Disease
Having a chronic disease does not mean that poor oral health is inevitable.
Follow these preventive measures:
- Brush twice daily with fluoride toothpaste.
- Clean between the teeth daily using floss, interdental brushes or another method recommended by your dentist.
- Attend regular dental examinations, particularly if you have diabetes or another condition that increases oral health risks.
- Control the underlying disease according to your physician’s treatment plan.
- Inform your dentist about all medications and supplements you take.
- Avoid tobacco products, as smoking significantly increases periodontal risk.
- Maintain a balanced diet rich in essential nutrients.
- Stay adequately hydrated, particularly if medications or disease cause dry mouth.
- Do not ignore bleeding or swollen gums.
Frequently Asked Questions
Can a medical condition cause gum disease?
Yes. Conditions such as diabetes and certain immune or blood disorders can increase susceptibility to periodontal disease or influence its severity. However, plaque-induced inflammation remains the primary initiating factor for most periodontal disease.
Can gum swelling be a sign of another disease?
Sometimes. Unusual or severe gingival enlargement, spontaneous bleeding, persistent infections or delayed healing can occur with certain systemic diseases. These signs are not diagnostic on their own and require professional evaluation.
Can vitamin deficiency affect the gums?
Yes. Severe nutritional deficiencies can affect oral tissues. For example, severe vitamin C deficiency can cause swollen and bleeding gums and impaired wound healing.
Can hormonal changes cause gum bleeding?
Hormonal changes can increase the gingival inflammatory response to plaque. This can occur during puberty and pregnancy, among other hormonal changes.
Can periodontal disease affect diabetes?
Periodontal inflammation may adversely affect glycaemic control. Treating periodontal disease is therefore an important component of oral healthcare in people with diabetes, although it should not replace medical diabetes management.
Does every person with a systemic disease develop gum disease?
No. Systemic disease may increase susceptibility or influence disease severity, but periodontal disease is multifactorial. Oral hygiene, smoking, genetics, microbial factors and access to dental care also play important roles.
Should people with chronic diseases visit the dentist more often?
The appropriate recall interval depends on the individual’s oral health, periodontal status, systemic disease and risk factors. People with increased periodontal risk may require more frequent professional monitoring.
Can improving oral health improve overall health?
Maintaining good oral health is beneficial for overall health. In conditions such as diabetes, good periodontal care is particularly important because of the established two-way relationship between periodontal inflammation and glycaemic control.
Key Takeaways
Your mouth can reflect what is happening throughout your body.
Although dental plaque is the primary initiating factor in most gingivitis and periodontitis, systemic diseases can influence the body’s immune response, inflammation, tissue healing, saliva production and susceptibility to infection.
Diabetes, immune disorders, blood diseases, hormonal changes, nutritional deficiencies and several other conditions can therefore influence periodontal and oral health. At the same time, chronic periodontal inflammation may have systemic effects and is particularly important in the management of diabetes.
The key message is simple: healthy gums are part of a healthy body.
Maintaining good oral hygiene, controlling underlying medical conditions, reviewing medications with healthcare professionals and attending regular dental examinations can help prevent complications and identify problems at an early stage.
Glossary
- Periodontal disease: commonly known as gum disease, a chronic inflammatory condition affecting the tissues that support the teeth.
- Pregnancy gingivitis: Pregnancy can increase gingival sensitivity to plaque; this is commonly referred to as pregnancy gingivitis.
- Osteoporosis: characterised by reduced bone mass and deterioration of bone tissue.
- GERD: occurs when stomach contents repeatedly flow back into the oesophagus.
- Dental erosion: erosion results primarily from chemical dissolution by acids rather than bacterial acid production.
- Sjögren syndrome: can reduce salivary gland function and cause persistent dry mouth.
References
All links checked and working on 28 September 2026.
- National Institute of Dental and Craniofacial Research (NIDCR). Periodontal (Gum) Disease. National Institutes of Health. NIDCR: Periodontal (Gum) Disease
- National Institute of Dental and Craniofacial Research (NIDCR). Diabetes and Oral Health. NIDCR: Diabetes and Oral Health
- American Academy of Periodontology. Gum Disease and Other Systemic Diseases. AAP: Gum Disease and Other Diseases
- Sanz M, Ceriello A, Buysschaert M, et al. Scientific evidence on the links between periodontal diseases and diabetes: Consensus report and guidelines of the joint workshop by the International Diabetes Federation and the European Federation of Periodontology. Journal of Clinical Periodontology. 2018;45(2):138–149.
- Tonetti MS, Greenwell H, Kornman KS. Staging and grading of periodontitis: Framework and proposal of a new classification and case definition. Journal of Periodontology. 2018;89(Suppl 1):S159–S172.
- Chapple ILC, Genco R. Diabetes and periodontal diseases: Consensus report of the Joint EFP/AAP Workshop on Periodontitis and Systemic Diseases. Journal of Clinical Periodontology. 2013;40(Suppl 14):S106–S112.
- Jepsen S, Caton JG, Albandar JM, et al. Periodontal manifestations of systemic diseases and developmental and acquired conditions: Consensus report of Workgroup 3 of the 2017 World Workshop. Journal of Clinical Periodontology. 2018;45(Suppl 20):S219–S229.
- Papapanou PN, Sanz M, Buduneli N, et al. Periodontitis: Consensus report of Workgroup 2 of the 2017 World Workshop on the Classification of Periodontal and Peri-Implant Diseases and Conditions. Journal of Clinical Periodontology. 2018;45(Suppl 20):S162–S170.
Disclaimer
This content is for educational purposes only and is not a substitute for professional medical or dental advice. Always consult a dentist, doctor or other qualified healthcare provider about any oral or general health concern, and before changing any medicine.

